Liver cirrhosis cannot usually be reversed, but the right treatment can slow it, prevent serious complications and help people live well for many years. This guide explains how cirrhosis is diagnosed and treated, and when an interventional radiologist can help. It is written for patients and families from Bhiwandi and the wider Thane–Palghar area.
What is liver cirrhosis?
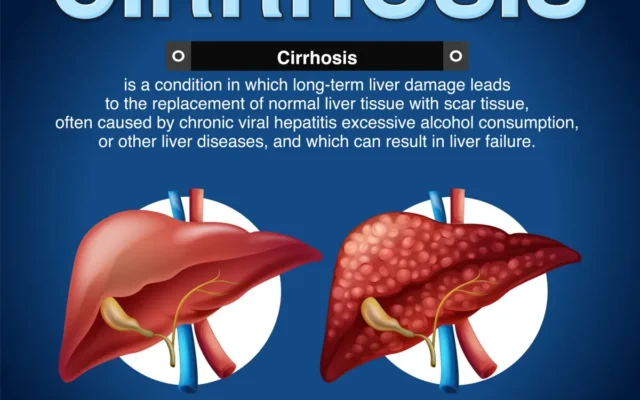
Cirrhosis is advanced scarring (fibrosis) of the liver. Healthy liver tissue is gradually replaced by scar tissue, so the liver works less well and blood flow through it becomes restricted. The most common causes are long-term alcohol use, hepatitis B or C, and fatty liver disease (MASLD/NAFLD). Autoimmune and inherited liver conditions are less common causes.
Cirrhosis develops in stages, from mild scarring to advanced disease. Read more in Understanding the Stages of Liver Cirrhosis.
Symptoms to watch for
Early cirrhosis often causes no symptoms. As it progresses, people may notice:
- Tiredness, weakness and loss of appetite
- Swelling of the abdomen (ascites) or legs
- Yellowing of the eyes or skin (jaundice)
- Easy bruising or bleeding
- Confusion or drowsiness (hepatic encephalopathy)
- Vomiting blood or black stools, which need emergency care
How cirrhosis is diagnosed
Diagnosis usually combines:
- Blood tests: liver function, clotting, blood counts and tests for hepatitis.
- Ultrasound and Doppler: show the liver’s size and texture, fluid in the abdomen, and blood flow in the portal vein.
- Elastography (FibroScan): measures liver stiffness without a needle.
- CT or MRI: used when more detail is needed, or to screen for liver cancer.
- Endoscopy: checks for enlarged veins (varices) in the food pipe or stomach.
- Liver biopsy: needed only in some cases. It can be done through the skin under ultrasound guidance or, when clotting is poor, through a vein in the neck (transjugular biopsy).
Treatment: the foundations
1. Treat the cause
Removing or controlling the cause is the most powerful step. That means stopping alcohol completely, taking antiviral medicines for hepatitis B or C, and managing weight, diabetes and cholesterol in fatty liver disease.
2. Diet and lifestyle
- No alcohol at all, whatever the cause of cirrhosis.
- A low-salt diet helps control fluid build-up.
- Enough protein and calories. Malnutrition is common in cirrhosis, so a late-evening snack is often advised.
- Stay active within your limits.
- Check with your doctor before taking painkillers, herbal or “liver tonic” products, as some can harm the liver further.
- Get vaccinated against hepatitis A and B if you are not already immune.
3. Medicines for complications
- Diuretics to reduce fluid in the abdomen and legs.
- Beta-blockers to lower pressure in the portal vein and reduce the risk of variceal bleeding.
- Lactulose and rifaximin to prevent and treat confusion caused by toxins building up.
- Antibiotics to treat or prevent infection of abdominal fluid.
When image-guided procedures help
Much of the danger in cirrhosis comes from portal hypertension: high pressure in the veins that carry blood to the liver. Interventional radiologists treat many of its complications through a needle or catheter, without open surgery.
- Paracentesis: ultrasound-guided drainage of fluid from the abdomen, to relieve tightness and breathlessness.
- TIPS (transjugular intrahepatic portosystemic shunt): a small stent placed inside the liver through a neck vein. It lowers portal pressure and is used for repeated variceal bleeding or fluid that keeps coming back despite medicines.
- BRTO and related procedures: block bleeding varices in the stomach from inside the vein.
- Transjugular liver biopsy: a safer biopsy route when blood clotting is poor or there is a lot of fluid.
- Liver cancer treatment: people with cirrhosis need an ultrasound about every 6 months to screen for liver cancer. If a tumour is found early, procedures such as ablation or TACE can treat it. See interventional oncology.
Whether you need any of these depends on your scans, blood tests and the advice of your liver specialist (hepatologist). Learn more on our liver cirrhosis and portal hypertension treatment page.
Liver transplant
When the liver can no longer support the body (decompensated or end-stage cirrhosis), a liver transplant may be the best long-term option. Transplant centres in Mumbai assess patients. Procedures such as TIPS can sometimes help keep a patient stable while they wait.
Follow-up and monitoring
- Blood tests and clinic reviews as advised, often every 3–6 months.
- Ultrasound every 6 months to screen for liver cancer.
- Endoscopy at intervals to check for varices.
- Prompt review if swelling, confusion, jaundice or bleeding appears.
Seek emergency care if you notice
Vomiting blood, black or tarry stools, sudden confusion or extreme drowsiness, a high fever with a painful swollen abdomen, or severe breathlessness. These can be life-threatening.
Consultation for patients from Bhiwandi
Dr. Chandrakant S. Kamble (MBBS, MD, DNB, FRCR(IIA), FVIR) is a vascular and interventional radiologist. He sees patients at Midas Sonography & Vascular Clinic, Ambadi Road, Vasai (W), and at partner hospitals across Vasai-Virar and Mira Road. He works alongside your hepatologist or physician on image-guided procedures for cirrhosis and portal hypertension. Bring your previous blood reports, scans and endoscopy reports to your visit.
Book a consultation or call +91 92092 32601.
This article is general information, not a diagnosis or a substitute for advice from your own doctor.